
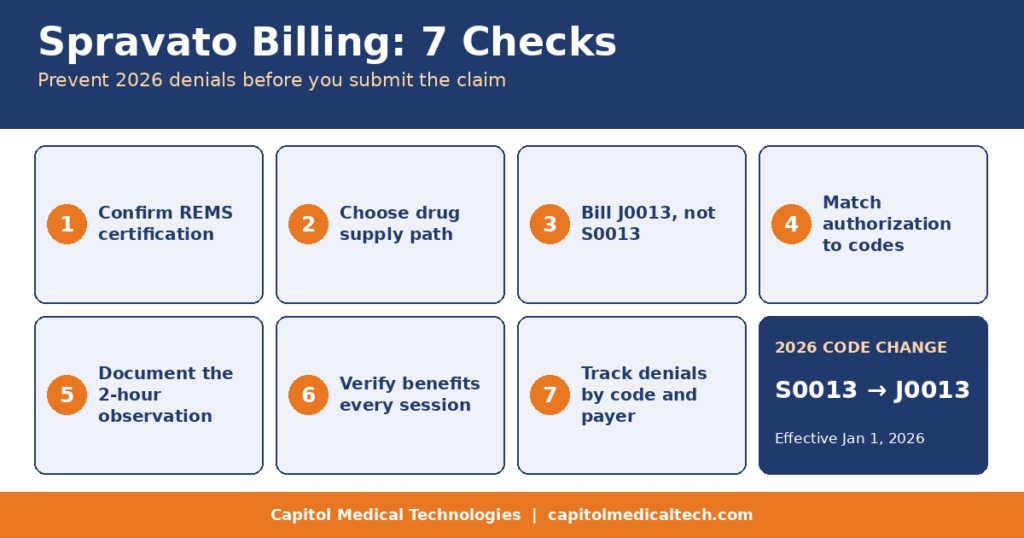
Spravato billing changed on January 1, 2026. According to the manufacturer’s coding guide, CMS retired the drug code S0013 and replaced it with J0013 (esketamine nasal spray, per 1 mg). Practices that still bill the old code, or still rely on old authorizations, can see rejections and denials.
Spravato billing is also harder than most office-based drug billing. Your practice needs REMS certification, a two-hour observation for every dose, and the right code path for how you get the drug.
This guide explains the 2026 codes, seven checks to run before you submit a claim, and the denial patterns to watch.
Spravato billing: 7 checks to prevent 2026 denials, including the S0013 to J0013 code change
Key Takeaways
- J0013 replaced S0013 on January 1, 2026. Update your charge master, fee schedule, and authorizations.
- Your code path depends on who supplies the drug: your practice, or a specialty pharmacy.
- G2082 and G2083 do not apply when a specialty pharmacy supplies the drug.
- Every session needs at least two hours of monitoring and a completed REMS patient monitoring form.
- Check each payer’s current policy. Some payers update codes more slowly than others.
What Is Spravato Billing?
Spravato (esketamine) is a nasal spray that patients self-administer under direct supervision. First Coast Service Options explains that outpatient settings must complete REMS certification, enroll each patient before the first treatment, and monitor patients for at least two hours after every dose.
So a Spravato claim has two parts: the drug, when your practice supplies it, and the supervised visit with observation. Three questions decide how you bill:
- Who bought the drug: your practice or a specialty pharmacy?
- Which payer will you bill: Medicare, Medicaid, or a commercial plan?
- Where does the patient receive treatment: a physician office or a hospital outpatient department?
If your practice also treats patients with TMS, our TMS billing guide covers that workflow.
Spravato Billing Codes for 2026
The manufacturer’s coding overview and Anthem’s coding tips describe these code paths. Anthem’s article dates from 2022, so use it for the structure of the service codes, not for the drug code.
| Code | What it covers | When it applies |
|---|---|---|
| J0013 | Esketamine nasal spray, 1 mg | Your practice buys the drug and bills it. The manufacturer’s guide lists 56 or 84 units for a 56 mg or 84 mg dose. |
| S0013 | Former drug code | Retired. Do not use it for 2026 services. |
| J3490 | Unclassified drug code | Some payers may still ask for it during the transition. Confirm each payer’s rule. |
| G2082 | Supervised self-administration visit, up to 56 mg, including two hours of observation | Your practice buys the drug. The manufacturer’s guide says Medicare requires G2082 and G2083 in this case, and other payers may require or accept them. |
| G2083 | Same service for doses over 56 mg (typically 84 mg) | Same as G2082. Do not use it when a specialty pharmacy supplies the drug. |
| E/M 99202–99205, 99212–99215 | Office visit | Payers that do not require the G codes, or visits where a pharmacy supplies the drug. Add the prolonged-service code your payer requires. |
| G0463 | Hospital outpatient clinic visit | Medicare hospital outpatient departments when a pharmacy supplies the drug. |
G2082 and G2083 combine the drug and the service, so do not bill the drug a second time on the same claim unless the payer tells you to. Payer rules vary and change often. Confirm the current policy before you bill.
7 Spravato Billing Checks Before You Submit a Claim
1. Confirm REMS Certification and Patient Enrollment
Check that your setting holds current REMS certification and that every patient enrolls before the first dose. Missing enrollment proof can stall payment and creates compliance risk.
2. Choose Your Drug Supply Path
Decide whether your practice buys and bills the drug or a specialty pharmacy supplies it. That choice controls which Spravato billing codes you can use. Ask each payer whether it covers Spravato under the medical benefit or the pharmacy benefit.
3. Bill J0013, Not S0013
Update your EHR, charge master, and fee schedule. Confirm your unit counts, because J0013 bills per milligram. Watch clearinghouse reports for rejections that stop claims before they reach the payer.
4. Match Your Prior Authorization to the New Code
Review every active authorization. If one lists S0013 or the wrong dose, ask the payer whether it needs an update or a new request. Payer policies usually ask for the diagnosis and prior treatment history, so read each policy before you submit. For help with this step, see our prior authorization services and prior authorization specialist guide.
5. Document the Two-Hour Observation
First Coast says the practice must record vital sign and safety checks on the REMS patient monitoring form and submit it after every session. It also asks for legible records with the patient’s name, dates of service, and the monitoring provider’s name. Record the dose, start time, end time, and observation results every time.
6. Verify Benefits Before Every Session
Coverage can change between sessions, especially at the start of a plan year. Confirm eligibility, copays, and authorization status before the patient arrives. Our guides on eligibility verification and what to check before every visit walk through the process. You can also hand this work to our eligibility and benefits verification team.
7. Track Spravato Billing Denials by Code and Payer
Report denials by payer, code, and reason every month. A pattern shows you which payer changed a rule and which front-desk step needs a fix. Read our claim denial rate guide and our list of revenue cycle KPIs to set up the reporting.
Common Spravato Billing Denials and How to Fix Them
| What you see | Likely cause | What to do |
|---|---|---|
| Claim rejects for the drug code | You billed S0013 for a 2026 date of service | Switch to J0013 and check the payer’s transition rule |
| Denial on G2082 or G2083 | A specialty pharmacy supplied the drug, or your practice did not supply it | Use the E/M path instead |
| Authorization does not match the claim | The authorization lists an old code, dose, or unit count | Ask the payer to update it before you resubmit |
| Request for records | The monitoring form, observation end time, or provider name is missing | Complete the REMS form every session and keep legible records |
| Coverage denial | The plan routes Spravato through the other benefit | Verify the benefit path before the first session |
If a Medicare contractor denies a claim, you generally must request a first-level appeal within 120 days. The CMS appeals booklet explains the process. For behavioral health appeals in particular, read our appeal guide and our list of common behavioral health denial reasons. Aged unpaid claims need their own routine, which our A/R follow-up guide explains.
Who Can Monitor Spravato Patients? State Rules Differ
The observation record supports your claim, so assign monitoring carefully. One example: Nebraska’s health department published an advisory opinion saying a medication aide may observe and report, but a licensed nurse practitioner must assess the patient after the dose and decide whether the patient is stable to leave. That opinion is informational and covers one state. Check your own state board before you delegate monitoring to staff.
Should You Outsource Spravato Billing?
Keep Spravato billing in-house when one trained person owns authorizations, REMS documentation, and denial follow-up. Consider help when:
- Authorizations or denials pile up faster than your team can work them
- Staff turnover leaves payer rules and documentation habits inconsistent
- Your practice adds Spravato to an existing behavioral health schedule and needs a process fast
Start with our medical billing services checklist and our guide to medical billing for small practices. If you outsource, sign a business associate agreement first. HHS explains that the HIPAA Rules generally require contracts between covered entities and their business associates. You can also outsource one queue, such as authorizations or denials.
How CMT Supports Spravato Billing
Capitol Medical Technologies (CMT) helps independent practices with behavioral health billing, medical billing and RCM, prior authorization, and denial management. We begin each engagement by documenting your scope, systems, payer mix, and escalation rules. We work inside your approved systems, use Business Associate Agreements where applicable, and charge no setup fees and require no long-term contracts.
Authorization tracking matters in behavioral health. On our homepage, a three-location behavioral health organization describes how standardized workflows and authorization tracking brought its denial rate from 19% to 4.8%. See that client outcome and our specialty practice RCM page. These results come from an anonymized engagement and do not guarantee future performance. Learn more about our HIPAA and security practices and our team.
Frequently Asked Questions
What replaced S0013 for Spravato billing?
According to the manufacturer’s coding guide, J0013 replaced S0013 on January 1, 2026. J0013 describes esketamine nasal spray, per 1 mg.
How long must you observe patients after Spravato?
The REMS requires at least two hours of monitoring after each dose. You must record the monitoring on the REMS patient monitoring form and submit it after every session.
Can you bill G2082 or G2083 when a specialty pharmacy supplies Spravato?
No. The manufacturer’s guide says you cannot use those codes when the drug comes from a specialty pharmacy. Use the E/M path your payer requires instead.
Do all payers accept J0013 yet?
Not necessarily. The manufacturer’s guide notes that some payers may still use J3490 during the transition. Check each payer’s current policy and review your authorizations.
Does CMT guarantee Spravato approvals or payment?
No. Payer rules, coverage, documentation, and coding all affect reimbursement. We provide disciplined workflow support and clear reporting, and we do not promise outcomes we cannot control.
The Bottom Line
Spravato billing rewards practices that treat the claim as a process, not a single code. Confirm your drug supply path, bill J0013, match your authorizations, and document every observation.
Start this week. Pull your active Spravato authorizations, check each for the old code, and test one claim per payer.
Want help with Spravato billing? Request a free revenue review with CMT.
Call: 571-410-3703 Email: info@capitolmedicaltech.com
This article is general information, not coding, legal, or medical advice. Code and payer rules change often. Confirm current requirements with each payer before you bill. Reviewed October 24, 2026.
Sources and Further Reading
- Manufacturer’s drug and procedure coding overview for Spravato
- First Coast Service Options: Spravato place of service and REMS requirements
- Anthem: Coding tips for reporting administration of Spravato (2022)
- Nebraska DHHS: Advisory opinion on esketamine direction and monitoring
- CMS: Medicare Part B appeals process (MLN booklet)
- HHS: Sample business associate agreement provisions